
Тайванийн судлаачдын хийсэн шинэ судалгаагаар сэтгэл гутралын эсрэг SSRI бүлгийн эм хэрэглэдэг хавдартай өвчтөнүүдийн дунд нас баралтын түвшин харьцангуй бага байгааг тогтоожээ.
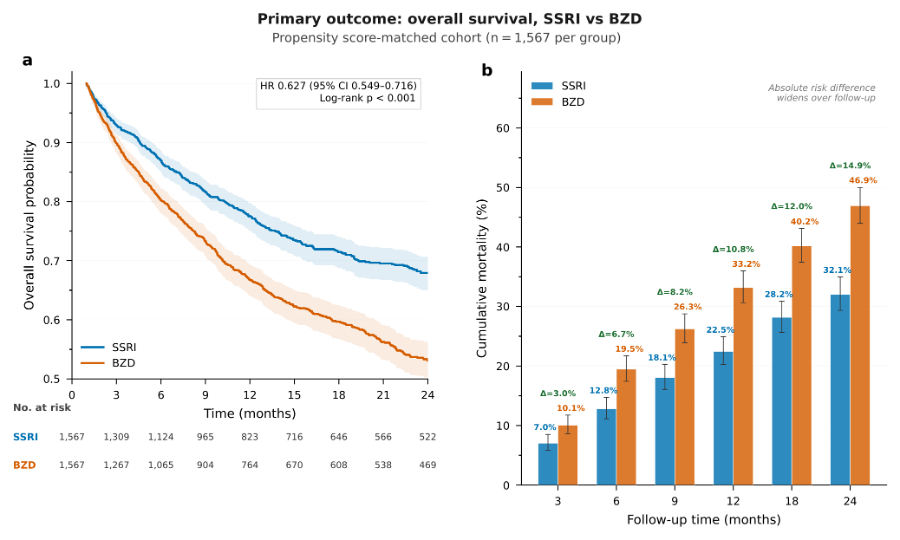
Тайванийн Tri-Service General Hospital болон National Defense Medical University-ийн эрдэмтэд 2015-2025 оны хооронд дархлаа эмчилгээ (immune checkpoint inhibitors) хийлгэсэн өвчтөнүүдийн эрүүл мэндийн цахим бүртгэлд дүн шинжилгээ хийжээ. Судалгаанд сэтгэл гутрал болон түгшүүрийн эмгэгтэй, хатуу хавдартай 1,567 SSRI хэрэглэгчийг ижил төстэй шинж чанартай, бензодиазепин хэрэглэдэг 1,567 өвчтөнтэй харьцуулсан байна. Үр дүнд нь SSRI бүлгийн эм хэрэглэсэн бүлэгт хоёр жилийн хугацаанд нас барах эрсдэл 37 хувиар бага байжээ.
Судлаач Cho-Hao Lee-ийн тайлбарласнаар, SSRI эмүүд нь дархлааны эсүүдийн үйл ажиллагаанд саад болдог механизмыг сулруулж, хавдрыг эсэргүүцэх дархлааны хариу урвалыг дэмждэг байж болзошгүй юм. Мөн серотонин дамжуулагч уураг нь хавдрын эсрэг тэмцэгч Т-эсийн үйл ажиллагааг дарангуйлдаг болохыг өмнөх судалгаанууд харуулсан бөгөөд уг эмийг хэрэглэх нь энэхүү дарангуйллыг бууруулах боломжтой гэж эрдэмтэд таамаглаж байна.
Гэсэн хэдий ч судалгаа нь ажиглалтын шинжтэй тул антидепрессант эмүүд хавдрын явцыг шууд удаашруулж байна гэж дүгнэх боломжгүй юм. Судалгааны багийн ахлагч Po-Huang Chen болон бусад судлаачид энэ нь өвчтөнүүдийн сэтгэцийн эрүүл мэндийн цогц тусламж үйлчилгээтэй холбоотой байх магадлалтайг тэмдэглэжээ.
Энэхүү судалгааны үр дүн нь эмнэлзүйн туршилт биш тул өвчтөнүүд өөрийн дураар эмчилгээндээ өөрчлөлт оруулах эсвэл дархлаа эмчилгээг дэмжих зорилгоор антидепрессант эхлэн хэрэглэх нь зохимжгүй гэдгийг мэргэжилтнүүд анхааруулж байна. Шинжлэх ухааны үндэслэлтэй баталгаажуулахын тулд цаашид санамсаргүй түүврийн аргаар хийх эмнэлзүйн туршилт шаардлагатай байгааг PLOS Medicine сэтгүүлд нийтлэгдсэн уг судалгаанд дурджээ.
Дэлгэрэнгүйг эх сурвалжаас харах
↓Эх сурвалжийг нээх ↓
Things that once brought pleasure lose their appeal. Getting out of bed, talking to friends, or finishing everyday tasks becomes harder. For someone living with depression, treatment can offer a way back into daily life.
People undergoing cancer treatment can also experience depression or anxiety, taking medication for their mental health alongside drugs aimed at their tumors. Researchers are now investigating an unexpected connection between those treatments.
A new analysis found that patients taking common antidepressants had fewer deaths recorded over two years after beginning immunotherapy, a treatment that helps the immune system attack cancer.
“The simplest way to put it is that SSRIs may release a second brake on immunity that sits right next to the one checkpoint inhibitors release,” oncologist Cho-Hao Lee of Tri-Service General Hospital and National Defense Medical University in Taiwan told ScienceAlert.
SSRIs, short for selective serotonin reuptake inhibitors, block the reuptake of serotonin, a chemical messenger. The group includes fluoxetine, sertraline, and escitalopram.
To investigate their potential connection with cancer outcomes, researchers examined medical records of adults with depression or anxiety and solid tumors, excluding blood cancers.
All were beginning treatment withimmune checkpoint inhibitors. These immunotherapy drugs block signals that can stop immune cells from attacking tumors.
Led by physician Po-Huang Chen of Tri-Service General Hospital and National Defense Medical University, the research identified eligible patients through the TriNetX electronic health record network who began immunotherapy between 2015 and 2025.
In thestudy, 1,567 SSRI users were matched with 1,567 people taking benzodiazepines, medications prescribed for problems including anxiety and insomnia. Matching covered 49 baseline characteristics, including demographics, tumor characteristics, other illnesses, medications, and laboratory results.
The aim was to compare patients who were as similar as possible. The main comparison therefore involved two psychiatric medication groups, rather than antidepressant users versus people taking no psychiatric medication.
Within the two-year outcome window, 368 patients in the SSRI group died, compared with 539 in the benzodiazepine group: 23.5 percent versus 34.4 percent.
An analysis accounting for when deaths occurred associated SSRI use with approximately a 37 percent lower hazard of death. That describes a lower relative rate of death during follow-up, rather than patients living 37 percent longer.
All five SSRIs that could be examined individually were associated with lower mortality. Compared with matched patients taking neither medication class, SSRI users had approximately a 25 percent lower hazard of death.
A possible explanation lies inserotonin’s effects beyond the brain. Cancer-fighting T cells also respond to this chemical messenger.
A2025 study published in Cellidentified the serotonin transporter, the protein SSRIs block, as a brake on these immune cells in mice. Blocking it strengthened antitumor immunity.
Combining an SSRI with anti-PD-1 immunotherapy, which releases another immune brake, improved tumor control. The new research investigates whether those laboratory findings might have a counterpart in patients.
The team separately analyzed 8,272 tumor samples from The Cancer Genome Atlas. Across 13 of 20 cancer types, higher expression of the gene encoding the serotonin transporter correlated with lower scores for T-cell inflammation.
However, these samples came from different patients than the cohort whose survival records the study assessed.
The findings support the proposed mechanism without showing that antidepressants changed conditions inside human tumors. Whether antidepressant doses alter serotonin levels or T-cell behavior within patients’ tumors remains unknown.
Medical records also revealed a difference in thyroid problems. Thyroid dysfunction was recorded in 31.6 percent of SSRI users, compared with 26.7 percent of benzodiazepine users. Hepatitis, pneumonitis, and colitis did not differ significantly.
Diagnosis codes could not establish whether every thyroid event was immune-related, leaving another question for future research.
One major limitation was missing information about patients’ ability to carry out everyday activities, an important predictor of cancer survival.
Benzodiazepines can also be prescribed for acute anxiety or insomnia when cancer is worsening. Their users might therefore have been more seriously ill despite appearing similar in the recorded characteristics.
SSRI prescriptions could likewise reflect more comprehensive psychological and medical care rather than a direct effect on tumors. Lee acknowledges that these differences could explain a meaningful part of the association.
“Only a randomized trial can settle how much is cause and how much is confounding,” he says.
Patients were not randomly assigned to either medication in this study, so the findings cannot establish that antidepressants extend life.
Future trials would need to assess survival, cancer progression, and side effects, while tumor samples collected before and after treatment could reveal changes in immune activity.
Researchers would also need to establish which drug, dose, and treatment duration might help. Including patients without depression or anxiety could help separate psychiatric treatment effects from potential anticancer effects.
For patients, Lee’s message is clear: “This is not a reason to start an SSRI to ‘boost’ immunotherapy, or to stop a benzodiazepine on your own.”
The research has been published in PLOS Medicine.
This article was fact-checked by Rachel Garner and edited by Rebecca Dyer. While we pride ourselves on our process, we are only human. If you spot a mistake, please let us know.

